As you go through The Defender’s
analysis on how the CDC lies via twisted and bad data conclusions to American
gullible Sheeple to entice compliance, YOU need to ask yourself a question:
What is the CDC motive for lying? AND: Who ultimately benefits from CDC lies?
One clue: the American can’t possibly benefit from CDC lies!
JRH 7/20/22
READER SUPPORTED! I need Readers willing to chip in $5 -
$10 - $25 - $50 - $100. PLEASE I need your generosity. PLEASE
GIVE to Help me be a voice for Liberty:
Please
Support SlantRight 2.0
Big Tech Censorship is pervasive – Share voluminously on
all social media platforms!
***************************
How CDC Blatantly Uses Weekly Reports to Spread COVID
Disinformation: Three Examples
The authors of the Centers for Disease Control and
Prevention’s Morbidity and Mortality Weekly Report are afforded the luxury of
broadcasting their findings to massive audiences through media outlets that
don’t hold them accountable for even gross lapses in scientific rigor.
CDC
Weekly Disinformation
By Madhava
Setty, M.D.
July 19, 2022
The
Defender
The Centers for Disease Control and Prevention (CDC) — the
primary U.S. health protection agency — publicly pledges, among other things,
to “base all public health decisions on the highest quality scientific data
that is derived openly and objectively.”
The CDC’s “primary vehicle for scientific publication of
timely, reliable, authoritative, accurate, objective, and useful public health
information and recommendations,” according to the agency,
is its Morbidity and Mortality Weekly Report (MMWR).
The CDC states that the
MMWR readership consists predominantly of physicians, nurses, public health
practitioners, epidemiologists and other scientists, researchers, educators and
laboratorians.
However, these weekly reports also serve as the means by
which the agency disseminates its scientific findings to a much wider
readership through media outlets that inform hundreds of millions of people.
Though the CDC asserts its MMWRs reliably communicate
accurate and objective public health information, the reports are not subject
to peer review, and the data behind the scientific findings are not always
available to the public.
Moreover, when the media summarizes MMWR findings in
articles intended for the general public, they often omit or misrepresent
important details.
As a result, the reports often steer public opinion to a
level of certainty the authors of the reports themselves cannot justify — and
often, to incorrect conclusions.
As Marty
Makary M.D., M.P.H., and Tracy Beth Høeg M.D.,
Ph.D., recently revealed,
some officials within the CDC claim the heads of their agencies “are using weak
or flawed data to make critically important public health decisions, that such
decisions are being driven by what’s politically palatable to people in
Washington or to the Biden administration and that they have a myopic focus on
one virus instead of overall health.”
In this article, I will demonstrate how the CDC used three
key MMWRs to compel the public to comply with pandemic response measures.
These reports were flawed to an extent suggesting more than
mere incompetence or even negligence — they were deliberate attempts by CDC
scientists to mislead the public.
These MMWRs address the effectiveness
of mask mandates (March 5, 2021), vaccine
safety during pregnancy (Jan. 7, 2022) and the risk of COVID-19 in
children (April 22, 2022).
Do I need to wear a mask?
The New York Times in May ran this story,
“Why Masks work, but Mandates Haven’t,” in which the author concluded:
“When you look at the data on
mask-wearing — both before vaccines were available and after, as well as both
in the U.S. and abroad — you struggle to see any patterns.”
But that’s not what the CDC concluded in its March 5,
2021, MMWR:
“Mask mandates were associated
with statistically significant decreases in county-level daily COVID-19 case
and death growth rates within 20 days of implementation.”
How could the CDC claim there was a statistically
significant decrease in cases within 20 days of mask mandate implementation if
there were no patterns in the data?
The explanation is necessarily detailed because the CDC
authors’ methodology is so devious. A detailed critique of the agency’s
approach is offered in this preprint
paper (Mittledorf, Setty) which I will summarize here.
The CDC researchers examined the number of COVID-19 cases
reported each day in each U.S. county that implemented a mask mandate.
Then they calculated the Daily Growth Rate (DGR) of cases
(and deaths) in each county on each day for 60 days preceding the countywide
mandate and for 100 days afterward.
The authors purportedly showed the DGR fell after mandates
were imposed. It is important to realize that when the DGR falls on a certain
day, it does not mean that fewer new cases occurred on that day compared to the
day before — it means the number of new cases is not growing as fast as it was
prior to that day.
In other words, by using DGR as the measure of interest, the
authors can still claim a “significant decrease in COVID-19 case growth rate”
even if the number of new cases on a given day is larger than the day before.
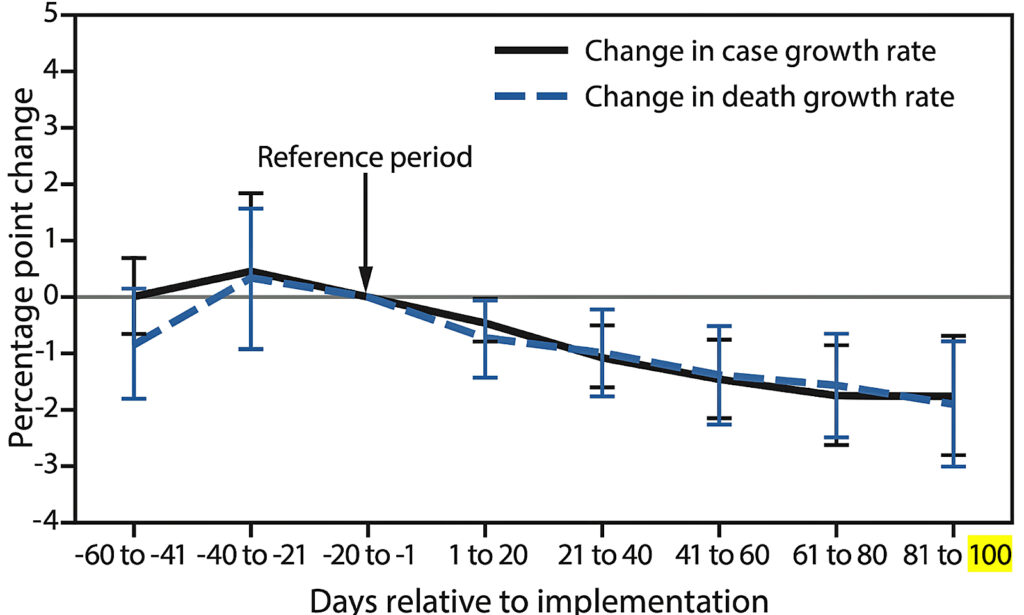
When data for 2,313 U.S. counties were tallied into a
composite graph, this is what they found:
change-case-death-growth-rate
Figure 1. Image credit: CDC
Note that mandates were implemented at different times in
different counties, so the “reference period” occurred at different times
during the year depending on the county.
Furthermore, the plot indicates the DGR at different times
relative to the DGR at the reference period.
In other words, when the plot falls below zero it does not
mean the DGR is negative — it means it was less than it was during the 20 days
prior to the institution of the mandate (the “reference period”).
Nevertheless, it seems that on average, the DGR falls after
the implementation of mask mandates.
However, what was happening prior to the reference period?
We don’t know — and neither do the authors of the CDC
report.
Figure 1 includes ranges of confidence intervals that
stretch above and below that of the reference period prior to mask mandate
implementation. Because the upper bound of the DGR is greater than the
reference period prior to the point mandates were implemented, it is entirely
possible the DGR was already in decline prior to the implementation of mask
mandates.
The authors’ own data and calculations demonstrate the drop
in DGR may have had nothing to do with mask mandates at all.
In other words, the authors also could have concluded mask
mandates were associated with a drop in the DGR 40 days prior to their
implementation.
In fact, this is clearly demonstrated in the graph. The DGR
for both cases and deaths is highest in the period 20 to 40 days before the
mandate.
How amazing! Masks seem to work several weeks before people
are forced to wear them!
Beyond ignoring what their own data suggested, the CDC
authors made two very suspicious decisions when designing their study.
The CDC chose to limit its analysis to 100 days after
mandates were instituted. Was this an arbitrary length of time? Or was there
another reason?
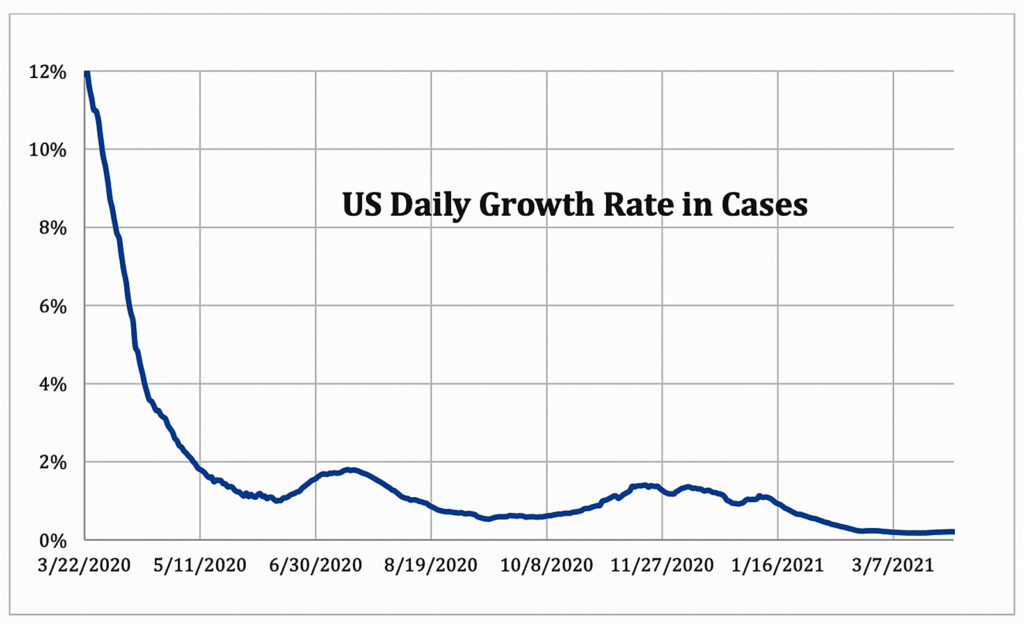
We examined data from the entire country for the period of
the study and plotted the DGR for a full year here:
U.S.
Daily Growth Rate Cases Figure
2
Figure 2 clearly demonstrates the DGR was already in steep
decline at the beginning of the study period, just as pointed out earlier.
The graph also indicates the DGR temporarily rose at the
beginning of the summer, then fell, then began to rise again at the beginning
of the autumn.
Because the overwhelming majority of mask mandates began in
the late spring and early summer, a 100-day window of analysis will show a
declining DGR because it will miss the increase in DGR in the fall.
Also note that a shorter period of observation, say 50 days,
would have resulted in equivocal or opposite findings as the summer “bump”
would have made it seem like mask mandates had no effect or possibly increased
the DGR.
The CDC conveniently chose an observational window that
could be neatly nestled between the periods of higher DGR.
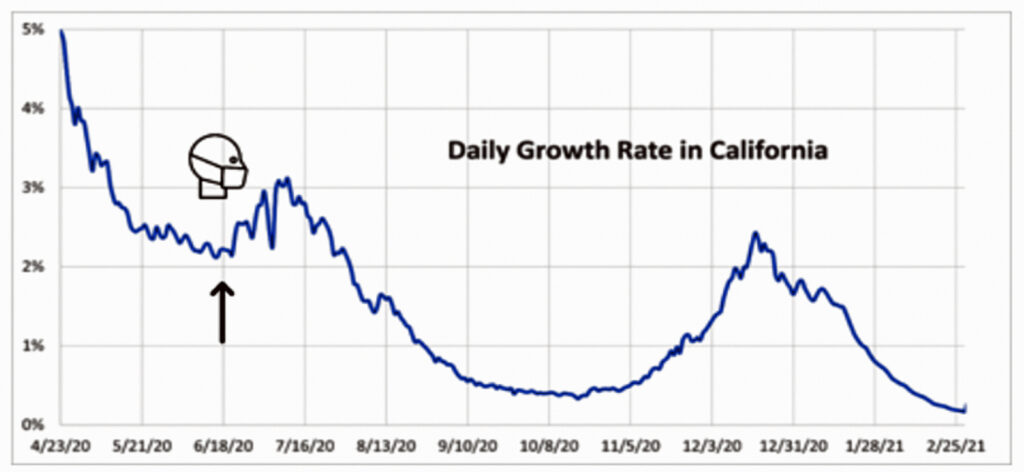
For example, the state of California imposed statewide
mandates on June 18, 2020. Using CDC data, this is what a plot of the DGR for
the state looks like if the period of observation were extended beyond 100
days:
Daily
Growth Rate California
Figure 3
The DGR at the end of the 100 days (Sept. 25, 2020) was
approximately 0.5%, or about 1.5% lower than it was prior to the mandates in
that state. However, two months later, the DGR had returned to its pre-mandate
level.
If the CDC extended its window of analysis it would not have
been able to claim there was any benefit from the mask mandates. The pattern
was similar in the country as a whole, as demonstrated in Figure 2.
Did the CDC just get lucky with its window of observation?
Or was the agency seeking a way to justify unpopular masking policies that had
been in effect for nearly a year at the time this study was released?
At this point, any reasonable researcher would suspect the
CDC’s authors were engaged in elaborate hand-waving to lead the public to a
predetermined conclusion.
How can we know for sure?
If the CDC were truly interested in demonstrating a fall in
the DGR due to mask mandates, the authors of the study would have asked the
most basic of questions: What happened in counties that did NOT institute mask
mandates during the study period? In other words, what happened in the
“control” group during the same time?
Though there were 829 U.S. counties that did not implement
mask mandates, the CDC researchers did not analyze any of them to test their
hypothesis. Why didn’t they?
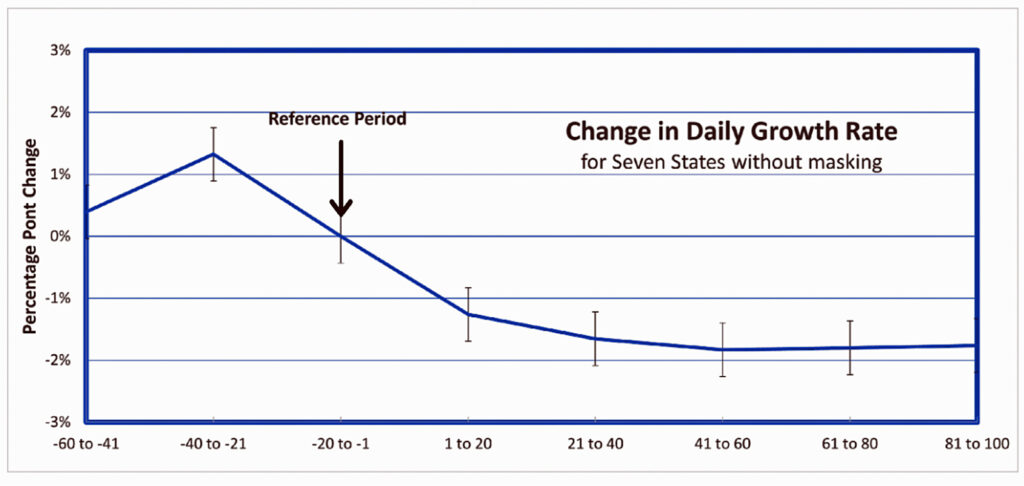
We did. From our preprint study linked above, this is what
we found:
[Counties NOT Implementing
Mask Mandate] Change
Daily Growth Rate Figure 4
Using publicly available data from the CDC and an arbitrary
“reference period” of Aug. 6, 2020 (roughly in the middle of the CDC’s study
period date), we calculated the DGR in counties of seven states without
mandates also fell to similar levels at the end of 100 days.
In other words, the decrease in DGR had nothing to do with
the imposition of mask mandates. It was due to a predictable pattern of any
infectious disease as it spreads through a population over time — whether or
not people were forced to wear masks.
This would have been obvious if the CDC were actually
interested in being scientific.
Nevertheless, the New York Times unhesitatingly covered the
CDC’s findings on the very same day the MMWR was released in
this article: “The Virus Spread Where Restaurants Reopened or Mask
Mandates Were Absent.”
The Times quoted CDC Director Dr. Rochelle Walensky who
said, “You have decreases in cases and deaths when you wear masks,” and Joseph Allen, an
associate professor at Harvard’s T.H. Chan School of Public Health, who said;
“The study is not surprising.
What’s surprising is that we see some states ignoring all of the evidence and
opening up quickly, and removing mask mandates.”
The Times wasn’t the only media outlet to report on the
flawed study.
CNBC posted
this article: “CDC study finds easing mask and restaurant rules led to more
Covid cases and deaths, as some states move to lift restrictions.”
And U.S.
News and World Report ran an article under this headline:
“Mask Use Associated With Decline in Coronavirus Cases, Deaths, CDC Says.”
In fact, more than 100 media
outlets cited the CDC study within 24 hours of its release —
but not one questioned the authors’ analysis.
In their defense, that is not their job. The media’s
role is to simply relay what the CDC has to say. Yet without any oversight or
accountability, the CDC can conclude whatever it chooses.
Because the mainstream media machine grants the CDC
infallible status, the public is lured into an illusion that “the science is settled.”
But why would the CDC authors go to such lengths to
manufacture an unfounded position on mask mandates? Surely they realized their
methodology would be scrutinized and found to be manipulative by those who
don’t consider the agency to be irreproachable. Why risk their credibility?
What do they have to gain?
The MMWR was released on a Friday. On the following Monday,
March 8, 2021, the CDC tells us, as NBC
News reported:
“‘As more Americans are
vaccinated, a growing body of evidence now tells us that there are some
activities fully vaccinated people can do,’ the CDC’s director, Dr. Rochelle
Walensky said during a White House Covid-19 briefing Monday.
“‘The latest science [emphasis
added],’ Walensky said, ‘suggests that fully vaccinated people can congregate
indoors with other fully vaccinated people without wearing face coverings or
practicing physical distancing.’”
And there you have it.
Three days after the flawed MMWR was released, being with
other human beings indoors without masks became a privilege reserved
exclusively for the “fully vaccinated.”
The “latest science” must demonstrate that masks offer some
protection, however miniscule. If there were no benefit to mask wearing, there
would be one less carrot authorities could use to get the public to comply with
their vaccine agenda.
Are COVID-19 vaccines safe during pregnancy?
In a Jan.
7 MMWR, the authors addressed another important public concern: Are
the vaccines safe during pregnancy?
To answer this question, CDC authors examined the incidence
of only two pregnancy outcomes: preterm births and small-for-gestational age
(SGA) in unvaccinated and vaccinated mothers.
They concluded:
“CDC recommends COVID-19
vaccination for women who are pregnant, recently pregnant (including those who
are lactating), who are trying to become pregnant now, or who might become
pregnant in the future to reduce the risk for severe COVID-19–associated outcomes.”
Their assurances came more than a year after the first
COVID-19 vaccine was granted Emergency Use Authorization, in
December 2020.
In this example, CDC authors did not have to cherry-pick
periods of observation or ignore control groups to make their “conclusions.”
Here, they relied on comparing two poorly matched groups of
mothers (the unvaccinated were at a higher risk of pregnancy complications):
·
There were greater than 50% more mothers in the
unvaccinated group classified as having inadequate prenatal care than in the
vaccinated group.
·
Obesity,
a risk for preterm birth, was also overrepresented in the unvaccinated group
(29% vs 23.9%) compared to the vaccinated.
·
There were greater than three times more African
American women in the unvaccinated group than in the vaccinated group. The CDC
acknowledges African American mothers may have as much as
a 50%
greater risk for preterm birth compared to white mothers.
·
COVID-19 infection, another potentially
important confounder, was present in the unvaccinated group at a 25% greater
incidence than in the vaccinated cohort. Viral infections early in pregnancy
are particularly deleterious to the developing fetus.
The differences between the two cohorts should have been
obvious to the authors. Why?
Because they found the risk of preterm birth and SGA in the
vaccinated weren’t equal to that in the unvaccinated group — in fact, they were
lower (adjusted Hazard Ratios were 0.91 and 0.95 respectively).
These numbers were very close to being statistically
significant.
Amazing. Masks prevent the spread of the disease weeks
before they are mandated and now we find that the COVID-19 jabs aren’t just
safe, they can actually lower the risk of preterm birth and SGA!
Why didn’t the authors report that their data indicated that
COVID-19 vaccines somehow reduce the risk of these outcomes? Was it because the
data weren’t quite statistically significant?
Or was it because they didn’t want to draw attention to the
fact that the unvaccinated group was at higher risk for these outcomes to begin
with?
But the most glaring deficit in the CDC analysis was the
scarcity of vaccinated mothers who received a vaccine in the first trimester in
this study.
The risk of untoward outcomes (birth defects, miscarriages)
in pregnancy is greatest during the first third
of pregnancy, a time when crucial embryonic structures are
developing.
This is the period of time where maternal health is
particularly important and exposure to toxins, infections and certain medicines
must be minimized or eliminated entirely if possible.
Only 172 of more than 10,000 (1.7%) vaccinated mothers in
the study received a vaccine in the first trimester.
This was acknowledged by the authors who explicitly stated:
“Because of the small number of first-trimester exposures, aHRs (adjusted
Hazard Ratios) for first-trimester vaccination could not be calculated.”
If they could not calculate the risk of the vaccine in the
first trimester, on what basis could they assure the recently pregnant, those
who are trying to become pregnant and those who might become pregnant in the
future that this experimental intervention was safe?
They couldn’t — but they did anyway. And once again,
mainstream media outlets wasted little time in spreading the “good news”:
·
Boston.com (Jan.
18, 2022): “New study bolsters case for COVID vaccination during pregnancy.”
·
Medical
News Today (Jan. 11, 2022): “COVID-19 vaccination during
pregnancy not linked to adverse birth outcomes.”
·
Medscape (Jan.
12, 2022): “COVID-19 Vaccination During Pregnancy Not Linked to Complications
at Birth: US Study.”
And even on other continents:
·
Juta
Medical Brief, Africa’s Medical Media Digest (Jan. 12, 2022):
“COVID vaccination not linked to premature birth or unusually small babies —
CDC study.”
·
newKerala.com (Jan.
8, 2022): “Researchers say COVID-19 vaccine does not disrupt pregnancy.”
Even People magazine,
a go-to source for the latest in medical research and public health, helped
spread the CDC gospel: “COVID Vaccines Among Pregnant Women Are Not Linked to
Pre-Term Births, According to New Study.”
Should I vaccinate my child?
In this April 19 MMWR,
CDC authors compared the risk of hospitalization of 5- to 11-year-old children
from COVID-19 during three different time periods: pre-Delta, Delta and
Omicron.
By the end of the period of observation, Feb. 28, 2022, only
approximately 30% of children in this age group had received both doses of the
primary series of COVID-19 vaccines. The experimental product had been authorized
for these children four months prior.
Was this report a “reliable, accurate and objective”
publication of available data? Or was it an attempt to persuade parents to
inoculate their children by making contradictory statements and illogical
reasoning?
Read on and decide for yourself.
The April 19 report uses a different set of tactics to lead
the unwary reader to false conclusions. In this example, statements are made in
the text of the paper that are true, but also irrelevant or misleading.
From the CDC’s own data (Table 1),
among hospitalized children aged 5-11 who had laboratory-confirmed COVID-19,
more were admitted because of COVID-19 during the Delta wave (364) than during
the Omicron wave (160). These numbers were statistically significant.
Yet the authors did not mention this fact in their
discussion. Instead, they chose to compare the rate of hospitalization during a
single, one-week peak of each wave: 2.8 per 100,000 during Omicron, and 1.2 per
100,000 during Delta.
Clearly, it is the total number of hospitalizations that is
salient when assessing the risk of the predominant variant in circulation — not
the number during a brief period of each wave.
Intentionally or not, the authors suggested Omicron is even
more dangerous than Delta — which
is not true.
This same strategy was used in yet another MMWR (from
March 15, 2022) that sought to convince parents of children under age 5 to
inoculate their young children by comparing hospitalizations at the peak of each
wave rather than the total number of hospitalizations.
Dr. Meryl Nass dissects
that CDC report here.
What are parents to do if they believe Omicron is more
dangerous than the Delta variant? The answer is apparently obvious.
The authors of the April 19 MMWR extracted hospitalization
rates from 14 states for fully vaccinated and unvaccinated children in this age
group: Unvaccinated kids are 2.1 times more likely to be hospitalized than
those who were fully vaccinated.
Surely this should be enough to motivate the uncertain
parent. However, when there is a potential risk it is imperative to assess the absolute
risk of the intervention, not just the relative benefit.
In this case, the risk of hospitalization during the Omicron
wave was 19.1 per 100,000 in the unvaccinated compared to 9.2 per 100,000 in
the fully jabbed.
This means roughly 10,000 children had to be fully
vaccinated to prevent a single hospitalization — a striking number the CDC
authors did not mention.
In typical fashion, the CDC authors don’t mention the risk,
which is yet to be established, of the experimental vaccine.
Though the authors accurately reported on the aggregate
data, they mysteriously chose to include another statistic: 87% of hospitalized
children were unvaccinated.
How could roughly 7 of 8 hospitalized kids (87%) be
unvaccinated if the rate of hospitalization was only about double in the
unjabbed?
The answer is that most children (70% or more) hadn’t been
inoculated during this time. Why would they mention this true-but-misleading
statistic?
We can’t know with any certainty, but it certainly makes a
good talking point.
Forbes did not consider such questions when it ran this
piece the same day: “87% Of Kids Hospitalized With Covid
During Omicron Wave Were Unvaccinated, CDC Says.”
Other media outlets also fell into line and ran stories with
misleading headlines based on this MMWR:
·
The
World Business News: “Omicron Was More Severe for Unvaccinated
Children in 5-to-11 Age Group, Study Shows.”
·
Axios:
“CDC: 87% of children hospitalized during U.S. Omicron surge unvaccinated.”
·
BNN
Bloomberg ran this: “Unvaccinated Kids Bore Brunt of Omicron
Wave, CDC Report Says.” The title is not inaccurate. However, the very first
line of the story predictably reads: “Almost 90% of U.S. children hospitalized
for Covid during the omicron wave this winter were unvaccinated, according to a
government study.”
If you read these articles you will find they all
regurgitate the same misleading statements the CDC authors included in the text
of their report.
On this page,
there are dozens of articles titled (more or less) “Unvaccinated Children
Hospitalized at Twice the Rate During Omicron Surge: US Study.” All cite the
misleading MMWR.
The data that supported the fact that the unvaccinated
children were twice as likely to be hospitalized was found here
on the CDC website. The data from the MMWR study period has since
been updated.
This is what the numbers now show:
Covid
Hospitalization Vaccination Status Image credit: CDC
As of May 2022, in the 5-to-11 age group, there is a
difference of 0.88 hospitalizations (3.35 – 2.47) per month in every 100,000
kids between the unvaccinated and vaccinated.
This means more than 113,000 children in that age group must
receive both doses to prevent a single hospitalization per month.
In yet a final attempt to confuse the reader, the CDC
authors state up front in their highlighted “Summary”:
“Increasing COVID-19 vaccination
coverage among children aged 5–11 years, particularly among racial and ethnic
minority groups disproportionately affected by COVID-19, can prevent
COVID-19–associated hospitalization and severe outcomes.”
Read that statement closely. They clearly state that
increasing vaccination coverage in this age group can prevent severe outcomes.
Can they prevent severe outcomes? Maybe. But did they? Not
according to their data.
The authors later correct themselves in the body of the report:
“There were no significant differences for severe outcomes by vaccination
status.”
Which statement do you think the media outlets chose to
publish?
No limits to their treachery . . .
The CDC website describes its MMWR series here:
“Often called ‘the voice of
CDC,’ the MMWR series is the agency’s primary vehicle for scientific
publication of timely, reliable, authoritative, accurate, objective, and useful
public health information and recommendations.”
If the MMWR series is “the voice of CDC,” mainstream media
serves as its mouthpiece.
By working together, the CDC authors are afforded the luxury
of broadcasting their findings to massive audiences through media outlets that
will not — and
in many cases cannot — hold them accountable for even gross
lapses in scientific rigor.
In my opinion, these examples demonstrate something more
than honest mistakes. These are egregious misrepresentations of data that were
meant to deliberately mislead the public, public officials and the medical
establishment in order to galvanize support around unpopular mandates and push
the “safe and effective” narrative. [Blog Editor Emphasis]
There wasn’t a “statistically significant decrease in
COVID-19 case counts associated with mask mandates.”
There wasn’t enough data to recommend the COVID-19 vaccine
for mothers who recently became pregnant.
The data did not demonstrate that the COVID-19 vaccine can
prevent severe outcomes in children ages 5 to 11.
The common thread in all three of these cases is that an
uninformed reader of these reports will readily conclude that getting the jab
is the best way to return to normalcy or protect a young child or a pregnancy.
We can speculate that Big
Pharma’s insatiable thirst for profit is behind the CDC and
corporate media, but with tens of billions of dollars already earned, why are
they so desperate to keep the misinformation campaign going?
The most obvious answer is that they cannot afford not to.
From the initial adult vaccine trials conducted in the summer and fall of 2020
to the most recent trials in the pediatric population, all placebo recipients
were given the jab after just a few short months.
This resulted in only short-term efficacy and safety data.
Using trial outcomes alone, no long-term safety assessments can be made. If
there is a significant risk in the middle to long term, it can be estimated
only through observational studies in the population.
The unvaccinated millions and their enduring health will
stand as the biggest threat to the industry’s income stream and our health
authorities’ credibility.
Authors of the CDC MMWR series are not accountable to
anyone, including the CDC director who parrots their findings, or the public
who rely on captured media outlets to ask the right questions.
With this level of impunity, there are no limits to their
treachery. [Blog Editor Emphasis]
Image credit for Figures 2-4: Josh Mitteldorf and Madhava Setty.
The views and opinions expressed in this article are
those of the authors and do not necessarily reflect the views of Children's
Health Defense. [Blog Editor: I understand the reasoning for the CHD disclaimer,
but the bad science is so egregious CHD should get behind this author’s
findings with a “YES! AMEN!”]
Madhava
Setty, M.D. is senior science editor for The Defender.
© 2016 - 2022 Children's Health Defense® •
All Rights Reserved.
The Defender HOMEPAGE